

‘Abstract
Background:
Monovalent COVID-19 vaccines targeting the XBB.1.5 Omicron variant were introduced in September 2023. In the absence of randomized controlled trials demonstrating their efficacy, information on real-world vaccine effectiveness (VE) is needed.
Objective:
To determine XBB.1.5 COVID-19 VE and the extent to which it declines over time.
Design:
Target trial emulation.
Setting:
U.S. Veterans Health Administration.
Participants:
Eligible XBB.1.5 vaccine recipients were matched 1:1 to unvaccinated persons in 7 sequential biweekly trials with enrollment from 2 October 2023 through 3 January 2024.
Intervention:
XBB.1.5 COVID-19 vaccination versus no XBB.1.5 vaccination.
Measurements:
Outcomes were ascertained through 10 May 2024 and included any positive result on a SARS-CoV-2 test from day 10 after the matched index date, subsequent hospitalization within 1 day before or 10 days after the positive result, or death within 30 days after the positive result. Vaccine effectiveness was estimated as 100 × (1 − risk ratio).
Results:
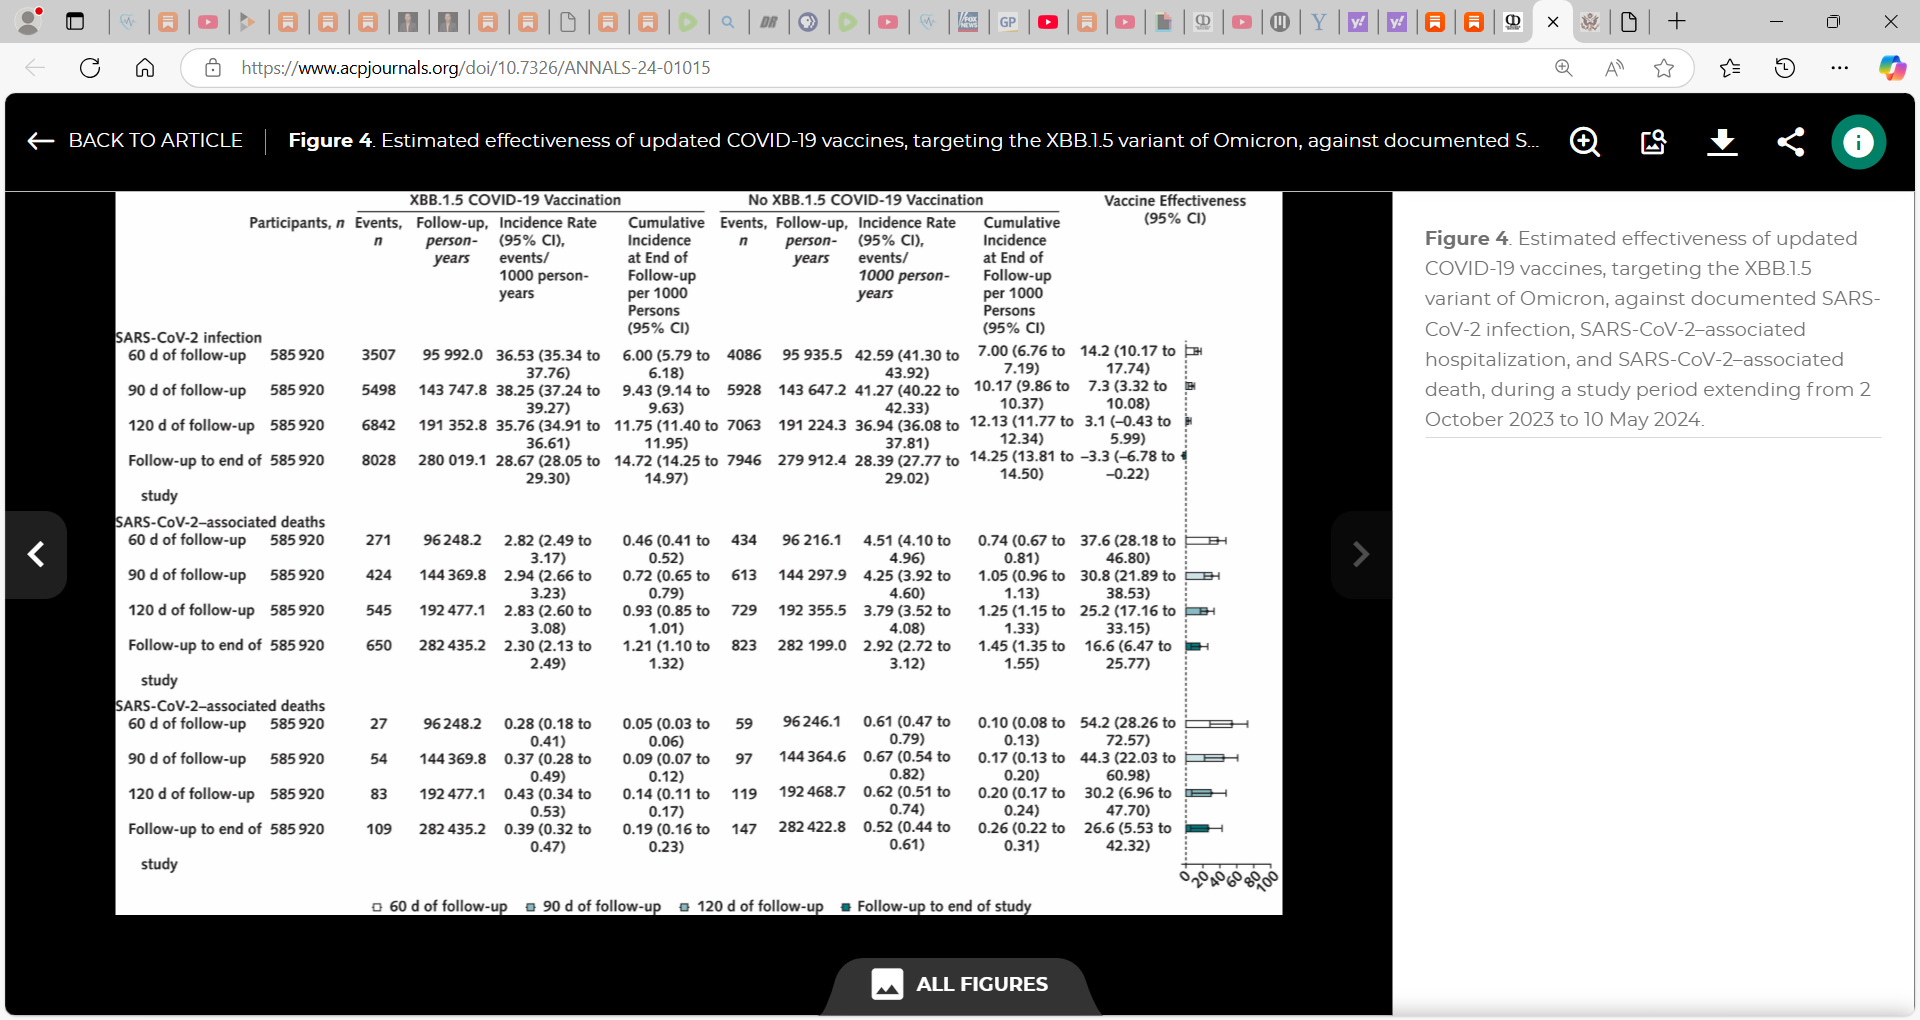
Participants (91.3% male; mean age, 69.9 years) included 587 137 pairs of vaccinated and matched unvaccinated persons. Over a mean follow-up of 176 days (range, 118 to 211 days), VE was −3.26% (95% CI, −6.78% to −0.22%) against documented SARS-CoV-2 infection, 16.64% (CI, 6.47% to 25.77%) against SARS-CoV-2–associated hospitalization, and 26.61% (CI, 5.53% to 42.32%) against SARS-CoV-2–associated death. When estimated at 60, 90, and 120 days, respectively, VE against documented infection (14.21%, 7.29%, and 3.15%), hospitalization (37.57%, 30.84%, and 25.25%), or death (54.24%, 44.33%, and 30.25%) showed substantial waning.
Limitation:
Potential for residual confounding and incomplete capture of COVID-19 vaccination and SARS-CoV-2–related outcomes.
Conclusion:
COVID-19 vaccines targeting the XBB.1.5 variant of Omicron were not effective in preventing infection and had relatively low VE against hospitalization and death, which declined rapidly over time.’
Declining VE Over Longer Follow-up
Vaccine effectiveness against documented infection progressively declined when ascertained after 60, 90, and 120 days of follow-up (14.21%, 7.29%, and 3.15%, respectively) and was even lower (−3.26%) when extended to the end of follow-up on 10 May 2024, corresponding to a mean follow-up of 176 days (Figure 4). Similarly, VE against SARS-CoV-2–associated hospitalization progressively declined when ascertained after 60, 90, and 120 days of follow-up (37.57%, 30.84%, and 25.25%, respectively) and was even lower (16.64%) when extended to the end of follow-up. Vaccine effectiveness against SARS-CoV-2–associated death progressively declined when ascertained after 60, 90, and 120 days of follow-up (54.24%, 44.33%, and 30.26%, respectively) and was even lower (26.61%) when extended to the end of follow-up.
Subgroup Analyses, Sensitivity Analyses, and Negative Control Outcome
During the entire follow-up period, VE against hospitalization (29.70%, 15.65%, and 14.39%) or death (83.62%, 27.20%, and 23.27%) decreased with older age (18 to 64, 65 to 74, and ≥75 years, respectively) (Supplement Figure 3). Vaccine effectiveness against hospitalization (8.50% and 22.16%) and death (5.30% and 36.11%) increased with increasing time since last vaccination (3 to 12 months and >12 months, respectively) (Supplement Figure 3).
The VE against SARS-CoV-2–associated hospitalizations occurring within 1 day before or after the test-positive date (VE, 16.71% [CI, 4.99% to 27.28%]) was nearly identical to that determined using the prespecified window of −1 to 10 days (VE, 16.6% [CI, 6.47% to 25.77%]).
Per protocol analysis with follow-up extending to 10 May 2024 resulted in similar estimates of VE against infection (−5.89% [CI, −9.81% to −2.42%]), hospitalization (16.70% [CI, 6.46% to 26.56%]), and death (27.18% [CI, 5.00% to 43.54%]) (Supplement Figure 4). The values found in a per protocol analysis with VE ascertained after 60, 90, and 120 days of follow-up against SARS-CoV-2–associated hospitalization (38.17%, 31.46%, and 25.68%, respectively) or SARS-CoV-2–associated death (57.59%, 47.75%, and 34.15%, respectively) were slightly higher than those in an intention-to-treat analysis but again showed a substantial decline in VE over time. Treating death as a competing risk resulted in almost identical VE estimates (Supplement Table 4).
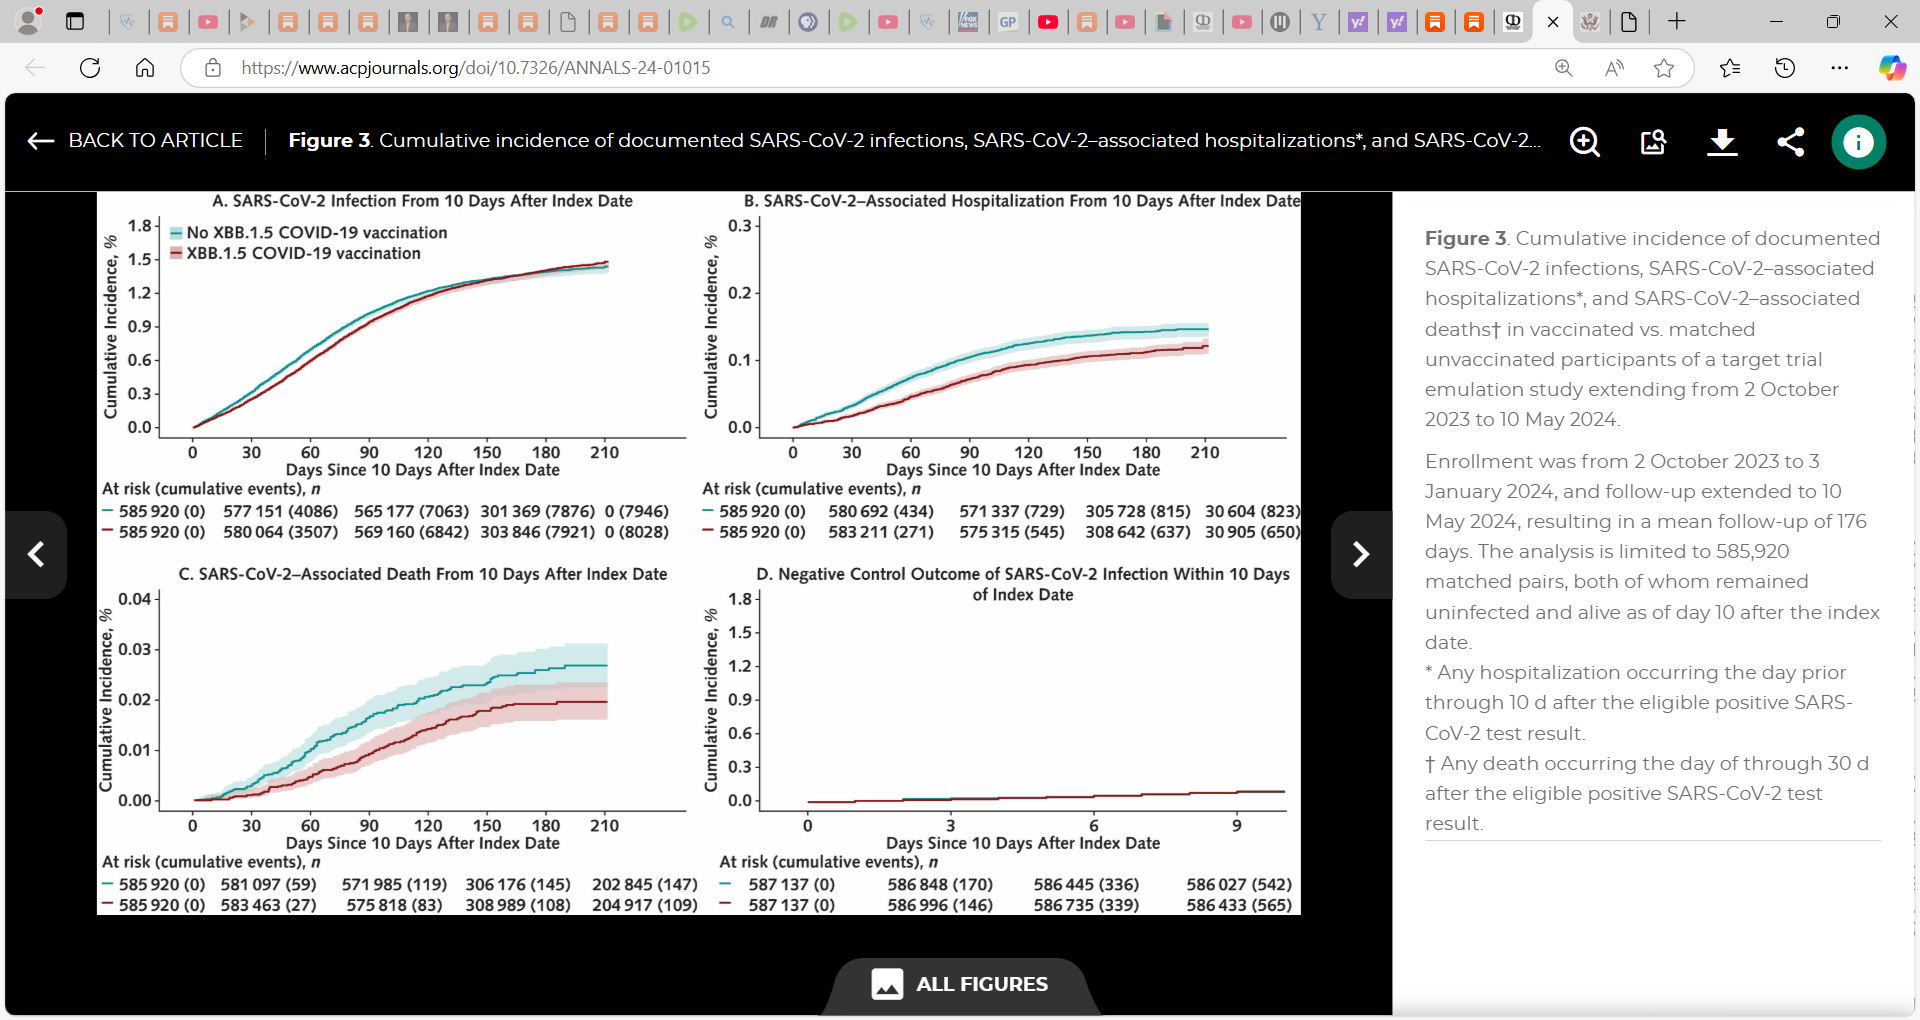
Our preselected negative control outcome (Figure 3, D), the rate of documented SARS-CoV-2 infections during the first 9 days after the index date, did not differ significantly between the vaccinated group (n = 620; cumulative incidence, 1.06 per 1000) and the unvaccinated group (n = 597; cumulative incidence, 1.02 per 1000) (risk difference, 0.04 [CI, −0.07 to 0.16]).
Discussion
Our target trial emulation study in the national VHA health care system between October 2023 and May 2024 among previously vaccinated veterans found that, over a mean follow-up of about 6 months, the COVID-19 vaccine targeting the XBB.1.5 variant of Omicron was not protective against documented SARS-CoV-2 infection and had relatively low estimated effectiveness against SARS-CoV-2–associated hospitalization (VE, 16.64%) and death (VE, 26.61%). Vaccine effectiveness estimated at 60, 90, and 120 days against documented infection (14.21%, 7.29%, and 3.15%, respectively), hospitalization (37.57%, 30.84%, and 25.25%, respectively), or death (54.24%, 44.33%, and 30.25%) showed modest early protection, which declined rapidly with time. Although updated vaccines targeting the KP.2 variant recommended for the current 2024-to-2025 respiratory season should be emphasized (4), particularly among vulnerable persons at high risk for COVID-19–related hospitalization or death, our findings call for accelerated efforts to develop new vaccination strategies that could provide higher and more sustained protection in the current era of COVID-19.’
___
You must not wait for another catastrophic crisis (at times manufactured but we are prevented from making our own basic personal decisions or accessing needed drugs and response tools) to catch you off-guard. We must take charge and be prepared today so that we can enjoy peace of mind tomorrow.
Enter the Wellness Company as a solution and a willing participant in the health care conversation. From telemedicine, prescriptions, memberships, and supplements, TWC is leading America with alternative choices to the traditional health care model.
If you wish to give a donation to help me, you can at:
Zelle:
sr7283@gmail.com
Or Ko-Fi
Ko-fi.com/drpauleliasalexander
Or to my address at:
150 South 8th Street
Unit 170
Lewiston, New York
14092
Alternatively, please consider going from an UNPAID subscriber or follower to a PAID at $5 per month or $30 per year. This can provide me help. If this is not possible at this time, this is ok, please remain a subscriber for FREE and there is no difference between FREE and PAID. No restrictions.
Please consider support of a good PATRIOT company (in this PATRIOT economy) Drs. McCullough, Risch, Thorp, myself support (they are our sponsors), The Wellness Company; see the emergency preparation kit (key component being antibiotics you were denied by doctors, pharmacists, governments during the fraud COVID), first aid kit, travel emergency kit, contagion control kit etc. Please consider the SPIKE SUPPORT (spike protein DETOX dissolving spike from mRNA vaccine, this is critical to remove spike form the mRNA vaccine/and DNA viral vector) formula with NATTOKINASE as well as the triple formula (SPIKE SUPPORT, BROMELAIN, CIRCUMIN)
Please stop the character assassination. You know who Bobby is. Unlike the moronic DEM Senators, you know his writings and the seminal resource that CHD is. So why did Bobby say disingenuous things to “the enemy?” What is the strategy? Your take in this is as welcome as anyone’s. But to infer that his head is planted where the sun don’t shine is, IMO, misleading and counterproductive.
Celia Farber characterized this phenomenon as refusal to cast pearls before swine. Yes, I can see that. Ginger Taylor surmised that it leads to not only confirmation but to close private communication between Bobby and the likes of Senator Cassidy. The Truth, delivered by Bobby, will prevail in this process.
Here is another take. Remember Fred Meyer? He and two companions parachuted into the Alps near Innsbruck near the end of WWll. One of them was a Luftwaffe defector who led the group to his hometown where he was recognized immediately: “Dude, GET OUT OF SIGHT … NOW!” Family and friends provided Meyer, a German born boy from Brooklyn and a Jew, with papers as an officer on leave from combat. He drew a uniform and meal tickets from the quarter master, lived in the barracks, had dined with the officers where he learned all about Hitjer’s bunker in casual conversations.
Eventually Meyer was caught and beaten by the Gestspo, but he was rescued by Kommendant Hofe who needed a way to surrender Innsbruck just as the Americans were closing in. Before the Soviets got there. Meyer arranged the surrender.
Meyer of course survived the nasty beating but never betrayed his companions … especially the radio operator the Gestapo were trying to find.
In his conversations in the Officer’s dining room, Meyer did not tell his dinner acquaintances much about himself. How disingenuous he was! He LIED!
The Senate Commitee Hearings were Bobby’s time with the Gestapo, having parachuted into corporate captured enemy territory, looking to arrange the surrender of HHS. He said whatever was necessary to survive the beating..
The extent of apparent initial modest effectiveness of the Trump-Mengele/Malone-M.A.I.D mRNA Kill Shot against hospitalization and death in this VA funded study looks suspiciously high. Is the take home message to get frequently boosted?
"Limitation:
Potential for residual confounding and incomplete capture of COVID-19 vaccination and SARS-CoV-2–related outcomes."
Damn straight! Use of propensity scores doesn't really mimic a randomized controlled trial. It can only adjust for variables that are measured in the data, leaving any unknown and unmeasured confounding factors unaccounted for, potentially introducing bias into the results.
Biases in COVID-19 vaccine effectiveness studies using cohort design
"healthy user bias, healthy vaccinee effect, frailty bias, differential depletion of susceptibility bias, and confounding by indication ... outcome misclassifications ... misclassification biases ... urgency to publish quickly may have further influenced these biases or led to their oversight, affecting the validity of the findings ... data infrastructure.
Addressing and mitigating these biases is essential for accurate VE estimates ... Transparent communication about these biases and rigorous improvement in the design of future observational studies are essential."
https://pmc.ncbi.nlm.nih.gov/articles/PMC11557388/